Procedure Deep-Dive · September 16, 2026
EMFACE and Facial Muscle Stimulation: What High-Intensity Electrical Currents Actually Do to a Facial Muscle, Why That Is Not the Same Device Category as Skin Tightening, and What the Evidence Actually Supports
A new generation of devices promises a lifted, more defined face by running electrical current through the muscles under the skin rather than heating the skin itself, and the pitch borrows heavily from the body-sculpting devices that came before it. The mechanism is real and distinct from radiofrequency or ultrasound skin tightening, but the facial evidence base is thinner than the marketing implies, and knowing exactly what is and is not being measured is the difference between a reasonable add-on and an expensive disappointment.
By The Editorial Desk
11 min read
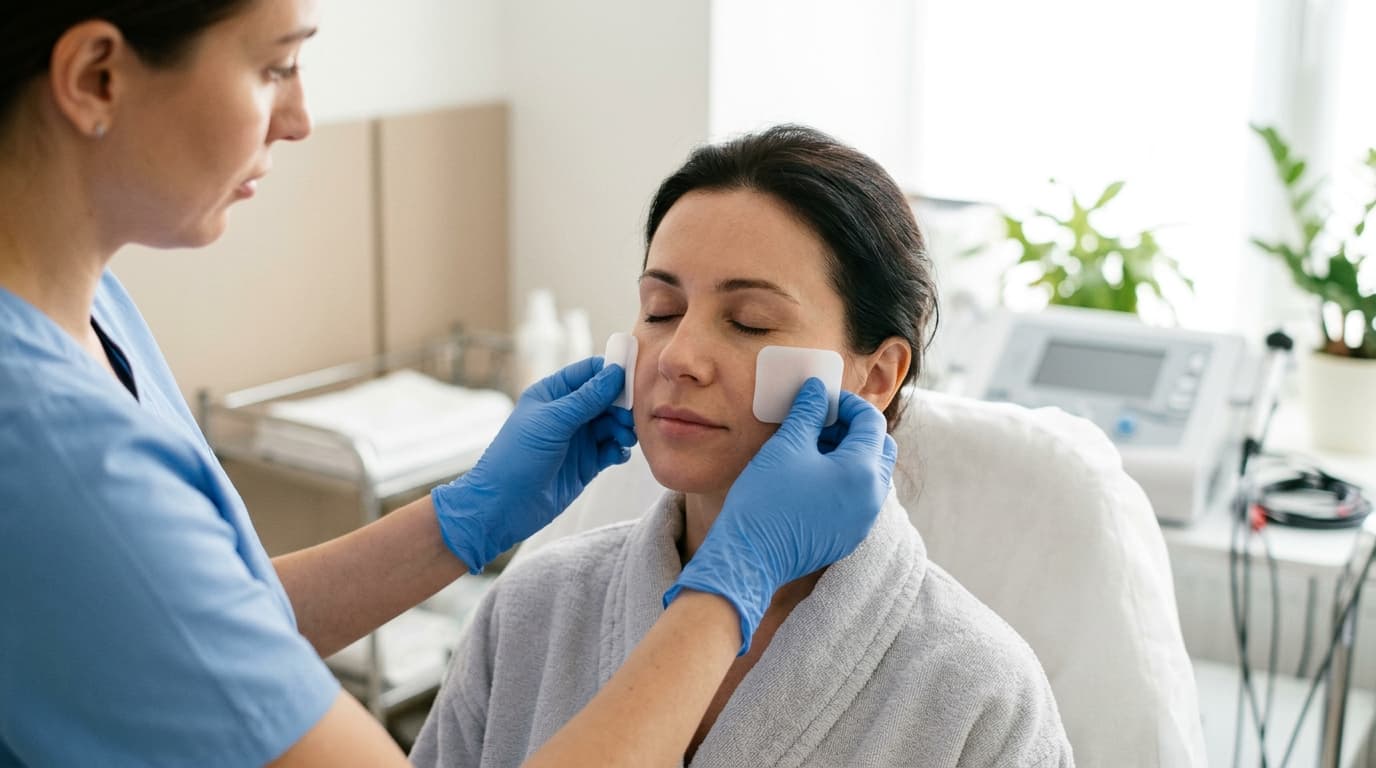
The body-contouring devices that stimulate muscle with electrical current have been in med spas for years, sold under names like Emsculpt for the abdomen and glutes, and the pitch was always about strength: a supramaximal contraction the patient could never produce voluntarily, delivered thousands of times in a half hour session, building muscle the way a very hard workout might. The newer generation of that same idea, aimed at the face, sells something different. Nobody is trying to sell a patient a bigger cheek muscle. The pitch is lift: a face that sits higher, an eyebrow that sits where it did a decade ago, a jawline that looks more defined, achieved by running current through the small, flat, sheet-like muscles that sit directly under facial skin rather than by heating the skin itself.
That distinction, current through muscle rather than heat into skin, is the entire reason this piece exists as its own category. This site has already covered what radiofrequency, microfocused ultrasound, and laser devices do when they heat the dermis to trigger collagen remodeling, in the piece on energy-based skin tightening, and what red and near-infrared light does at the cellular level in the piece on red light therapy. Facial electrical muscle stimulation, sold most prominently under the EMFACE name, is a different mechanism aimed at a different tissue layer, and it deserves to be evaluated on its own terms rather than folded into the broader "skin tightening device" conversation it gets lumped into in most marketing. Several devices in this category pair the muscle-stimulation current with a separate radiofrequency channel running at the same time, and that RF component belongs to the skin-tightening conversation already covered elsewhere on this site. What follows is specifically about the muscle-stimulation half: what it does to a facial muscle, what the evidence for that specific effect actually shows, and who is a reasonable candidate for it.
What facial electrical muscle stimulation actually is, and how it differs from the body version
The short answer: facial devices deliver current through electrode pads in direct contact with the skin, contracting the small mimetic muscles that create facial expression, while the body devices most people have heard of use a contactless magnetic coil to induce current in large, deep muscles like the rectus abdominis, and the difference in delivery method exists because facial muscles are a fundamentally different kind of tissue than abdominal or gluteal muscle.
The body technology, high-intensity focused electromagnetic stimulation, was cleared by the Food and Drug Administration in 2018 for strengthening and toning muscle, and the mechanism there is a magnetic field that never touches the skin, inducing a current in muscle bulk that sits several centimeters deep, as the piece on abdominal etching and the piece on non-surgical body contouring both describe. Facial mimetic muscles, the frontalis across the forehead, the zygomaticus major and minor that lift the corners of the mouth and cheek, and the muscles around the eye and brow, are not built like the rectus abdominis. They are thin, flat sheets that insert directly into skin rather than bulky, deep muscle groups, and a coil placed several centimeters away would not couple with them efficiently. The facial devices instead use electrode pads applied directly to the skin, delivering what the manufacturers describe as high-intensity focused electrical stimulation, a direct-contact current rather than an induced one, tuned to contract those specific thin muscles repeatedly over a treatment session. BTL Aesthetics, the company behind EMFACE, received FDA clearance in 2021 for a facial muscle-toning indication, the first clearance in this specific device category, and several competitors have since entered with similar direct-contact electrical stimulation designs.
This is a genuinely different mechanism from the muscle work done by a neuromodulator. Masseter Botox, preventative Botox, and the Nefertiti lift all work by weakening or partially paralyzing a targeted muscle, which is the opposite instruction to what an electrical stimulation device is trying to do. One category quiets a muscle down. The other is trying to make a muscle contract harder and more often than it would on its own. A patient considering both in the same season should understand that a stimulation device and a neuromodulator are not competing for the same job; in some treatment plans they are used on entirely different muscle groups for opposite reasons.
What supramaximal contraction actually does to a facial muscle, and why the facial evidence is thinner than the body evidence
The short answer: the biological premise, that repeated forced contraction can increase muscle fiber size and improve tone, is supported by a real body of research on the abdominal and gluteal muscles, but the facial-muscle evidence is smaller in volume, shorter in follow-up, and drawn almost entirely from studies funded or run by the device manufacturer, which is a meaningfully different evidence picture than a decade of independent body-contouring research.
The body literature on high-intensity focused electromagnetic stimulation includes independent histological studies, ultrasound-measured muscle thickness changes, and MRI-based volume measurements across several published papers with reasonable, though still modest, sample sizes, as the earlier pieces on this site have covered. That body of work is not perfect and it is heavily industry-supported, but it has had years to accumulate. The facial-muscle literature on high-intensity focused electrical stimulation is newer, smaller, and dominated by studies designed and funded by the manufacturer whose device is being tested, published in aesthetic and dermatology journals that specialize in device outcomes. That does not make the findings false. It does mean a reader should apply a heavier discount than to an independently replicated finding, and should notice when a study's authors are also device-company consultants or clinical advisors, a disclosure worth reading rather than skipping.
The mechanism itself is plausible on basic physiology. A facial muscle, like any skeletal muscle, can respond to repeated forced contraction with some degree of hypertrophy and improved tone, and a muscle that sits closer to its resting length and holds slightly more tone can, in principle, hold the soft tissue draped over it in a marginally higher position. The honest caveat is the word marginally. Facial mimetic muscles are small and thin compared to the rectus abdominis, the soft tissue they support is thinner than abdominal skin and fat, and the amount of lift physically available from muscle toning alone, without addressing the deeper structural descent that a deep plane facelift or a mini facelift corrects, is bounded by basic anatomy no matter how well the device performs its intended job.
"A muscle that holds a little more tone can hold the tissue over it a little higher. It cannot reposition tissue that has actually descended, and no amount of electrical current changes that.
"
What the published studies actually measure, and where the marketing runs past the data
The short answer: the strongest published outcomes for facial electrical stimulation devices are objective muscle thickness and skin measurements taken with imaging tools, the softer outcomes are patient satisfaction surveys and blinded photographic panel scores, and the gap between those two kinds of evidence is where most of the marketing language lives.
A manufacturer-supported study on EMFACE, published in a dermatology or aesthetic surgery journal, typically reports some combination of ultrasound-measured increase in the thickness of the treated muscles, a measured reduction in wrinkle depth or skin laxity attributed to the paired radiofrequency channel rather than the muscle stimulation itself, and patient-reported satisfaction scores collected at a follow-up visit weeks to a few months after the final session. The muscle-thickness findings are the most directly relevant to the muscle-stimulation half of this technology and are also the most modest in absolute terms, typically described as a measurable but small percentage increase. The skin and wrinkle findings belong mostly to the radiofrequency channel running alongside the stimulation, not to the muscle current itself, and folding those two effects into a single "lift" claim in advertising makes it hard for a patient to know how much of any visible change came from the muscle mechanism this piece is actually about.
Independent, non-industry-funded replication of the facial-muscle findings is limited, follow-up beyond roughly a year is sparse in the published literature, and there is no long-term data on what happens to muscle tone once a patient stops maintenance sessions, though the body literature on HIFEM devices suggests any gains fade over months without upkeep, a pattern the piece on abdominal etching documents directly for the body version of this mechanism. There is no strong reason to assume the facial muscles behave differently, and a patient budgeting for this category of treatment should plan for ongoing maintenance sessions as the honest cost of keeping any effect, not as an unexpected upsell.
Who is actually a reasonable candidate, and who is ruled out immediately
The short answer: the most reasonable candidate is someone with mild to moderate signs of facial aging who wants a subtle improvement in tone and position without surgery and without a long recovery, and the immediate exclusions are patients with implanted electronic devices, metal implants in the treatment area, active pregnancy, or a seizure disorder, because the current itself is the mechanism and it is not selective about what tissue it passes through.
A pacemaker, an implanted defibrillator, a cochlear implant, or any other implanted electronic device is an absolute contraindication, since an externally applied electrical current has the potential to interfere with an implanted one, and this is not a theoretical caution most clinics wave off; it is a standard exclusion criterion across every device in this category. Metal implants or permanent facial fillers in the direct treatment path raise similar concerns depending on the specific product and location, and pregnancy and epilepsy are standard exclusions consistent with how any electrical-current device is handled in a medical setting. Beyond the absolute exclusions, the realistic candidate is someone with early to moderate laxity who is a poor match for surgery on timing, budget, or appetite for downtime, not someone with significant jowling or neck laxity who is hoping a series of in-office sessions will substitute for what a deep plane facelift or a neck lift actually accomplishes structurally. A clinic that offers this device to a patient with significant tissue descent and calls it an alternative to surgery is selling a mismatch between the tool and the problem, the same pattern the piece on non-surgical facelift limits already describes for other device categories.
How this fits next to the other muscle-focused and lifting options
The short answer: facial electrical stimulation sits in a genuinely different category from neuromodulators, thread lifts, and surgical lifting, and the honest way to think about it is as a mild toning add-on rather than a competing alternative to any of the three, since each of those other options is solving a different structural problem.
A neuromodulator weakens a specific overactive muscle to soften a line or change a resting expression, the opposite instruction from a stimulation device, and the comparison between Botox and Dysport and the piece on trap tox cover that mechanism directly. A thread lift uses barbed sutures to mechanically hoist soft tissue along a defined vector, a completely different physical action than encouraging a muscle to hold more tone on its own, and the piece on whether PDO thread lifts actually work lays out how modest and temporary that mechanical lift tends to be in practice. Surgical lifting, whether a full deep plane facelift, a mini facelift, or the more conservative approach described in the piece on the quiet end of the pull-tight facelift, repositions the deep tissue layer directly rather than working through the tissue's own muscle tone, and remains the only category of these four that reliably addresses real descent. A patient evaluating a jawline concern specifically should also read the piece on jawline contouring at forty, which surveys the fuller set of options at that stage of aging, of which facial muscle stimulation is one modest entry, not the headline.
None of this makes facial electrical stimulation worthless. It makes it a small, real, temporary effect that belongs in the same honest conversation as the other non-surgical tools on this site, judged against what its own evidence actually supports rather than against a marketing photo that quietly borrows credibility from the mechanical lift a thread or a scalpel produces. The piece on reading a before-and-after gallery and the piece on plastic surgery satisfaction rates both apply here as directly as anywhere else on this site: ask what baseline the photos started from, ask how the satisfaction number was collected and by whom, and treat a manufacturer-funded study the way any reader should treat a study funded by the company whose product it is testing.
The honest summary
Facial electrical muscle stimulation is a real, distinct mechanism from the radiofrequency and ultrasound devices already covered on this site, delivering current directly to the thin mimetic muscles under facial skin rather than heating the dermis, and the underlying physiology, that forced repeated contraction can modestly increase muscle tone, is plausible and grounded in a more mature body of body-contouring research. The facial-specific evidence for that effect is newer, smaller, and mostly manufacturer-funded, the measurable muscle-thickness changes are modest, and any gain appears to fade without maintenance, consistent with what the body version of this technology already shows. It is a reasonable add-on for a patient with mild to moderate aging who wants a subtle improvement without surgery, and it is a poor substitute for surgery in a patient with real tissue descent, where only a structural lift changes the anatomy that actually moved. The marketing habit of blending the muscle-stimulation effect with a paired radiofrequency skin effect into one lift claim is the single most common way patients end up overestimating what either mechanism does alone. Ask which channel is doing what, ask to see the actual measurement rather than the satisfaction score, and budget for maintenance as part of the real cost from the start.